
Why Pain Exists
Pain is often thought of purely as something to eliminate, but it exists for a reason: it's the body's alarm system, a signal that something is wrong and needs attention. A hand pulled instantly from a hot stove, a limp that protects an injured ankle from further damage ??? these are pain doing exactly what it evolved to do. The trouble is that pain doesn't always stay useful. It can persist long after an injury has healed, or occur without any clear injury at all, and understanding why has taken centuries of scientific work.
How Pain Actually Works
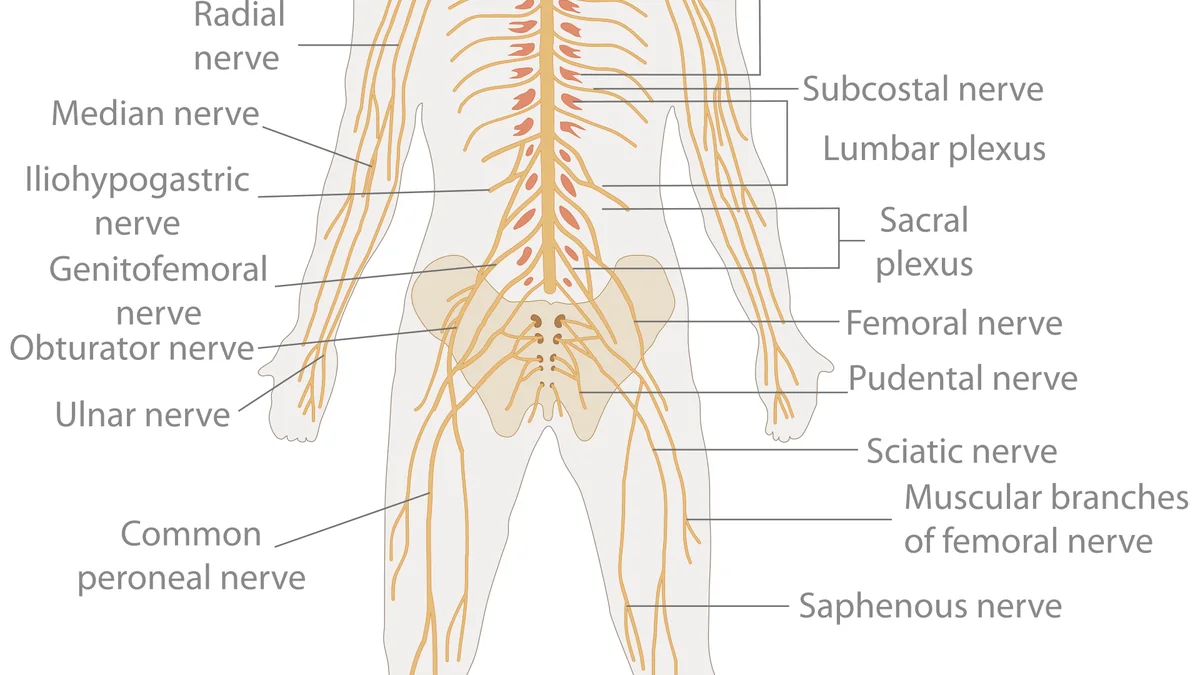
Pain begins with specialized nerve endings called nociceptors, found throughout the skin, muscles, joints, and internal organs. These nociceptors don't respond to every sensation ??? they're tuned specifically to detect potentially damaging stimuli: extreme heat or cold, intense pressure, or chemical signals released by damaged tissue. When triggered, they send an electrical signal along nerve fibers toward the spinal cord.
From there, the signal travels up the spinal cord to the brain, where it's processed by several different regions at once. This is a key point that's often missed: pain isn't simply registered in one place like a single sensor reading. The brain simultaneously processes the physical location and intensity of the signal, along with its emotional weight and context, which is part of why the same injury can feel more or less painful depending on a person's mental state, expectations, or circumstances.
A particularly important theory in understanding this was the "gate control theory" of pain, proposed in 1965 by researchers Ronald Melzack and Patrick Wall. It suggested that the spinal cord contains a kind of gating mechanism that can either amplify or dampen pain signals before they even reach the brain, influenced by other incoming nerve signals and by the brain's own descending signals. This helped explain long-observed but poorly understood phenomena, such as why rubbing an injured area can ease pain, or why intense focus or distraction can blunt it.
Acute Pain vs. Chronic Pain
Acute pain is a direct, time-limited response to injury or illness, and it typically resolves as healing occurs. Chronic pain is different, and in many ways more medically complex: it persists well beyond normal healing time, sometimes for months or years, and often involves changes to the nervous system itself. In chronic pain, nerve pathways can become sensitized, effectively turning up the volume on pain signals or continuing to send them even after the original cause has resolved. This is why chronic pain increasingly isn't treated simply as "acute pain that won't go away," but as its own distinct condition requiring a different approach.
A Long History of Trying to Answer It
Humans have been searching for ways to relieve pain for as long as recorded history exists. Ancient Egyptian, Chinese, and Greek medical texts describe pain remedies including willow bark, the natural source of the compound later refined into aspirin, and opium poppy extract, the origin of morphine and the broader opioid class of medicines still used today. For most of human history, these plant-derived substances, alongside practices like acupuncture in Chinese medicine, represented the primary tools available for pain relief.
A major turning point came in the 1840s with the development of surgical anesthesia ??? first with ether, then chloroform ??? which for the first time allowed pain to be eliminated entirely during surgery, rather than merely dulled. This transformed not just pain management but the entire practice of surgery, which had previously been sharply limited by what a conscious patient could endure.
The late 19th and 20th centuries brought the isolation and refinement of specific pain-relieving compounds: morphine was purified from opium in the early 1800s, aspirin was synthesized and marketed in the 1890s, and paracetamol and ibuprofen followed in the 20th century, giving physicians an expanding toolkit with different mechanisms and risk profiles to choose from.
Pain medicine also grew into its own recognized medical specialty over the latter half of the 20th century, formalizing what had often previously been treated as a side effect to manage rather than a condition in its own right, particularly for chronic pain.
Where Pain Management Stands Today
The most significant shift in recent pain management has been toward multimodal care ??? combining several different approaches, each working through a different mechanism, rather than relying on a single medication. This might mean pairing a non-opioid medication with physical therapy, psychological approaches like cognitive behavioral therapy, and targeted nerve-based treatments, addressing the sensory, emotional, and functional dimensions of pain together rather than in isolation.
This shift has been reinforced by a broader reckoning with the risks of long-term opioid use, which has pushed research and clinical practice firmly toward developing effective non-opioid alternatives. A notable recent example is the 2025 approval of a new class of non-opioid pain medication that works by targeting a specific pain-signaling pathway in nerves rather than acting on the brain's opioid receptors, offering meaningful pain relief for acute pain without opioid-related risks.
Alongside new medications, neuromodulation techniques ??? including spinal cord stimulators and other devices that directly influence nerve signaling ??? have become an increasingly established option for chronic pain that doesn't respond well to medication alone. There's also a growing emphasis on personalized, diagnosis-driven care, recognizing that two people with what looks like the same pain complaint, such as back pain, may have entirely different underlying causes requiring different treatment approaches.
A Field Still Evolving
What's changed most over the long history of pain treatment isn't just the tools available, but the understanding behind them. Pain has gone from being treated as a simple, singular sensation to be blunted, to being understood as a complex signal shaped by the nervous system, the brain, and individual context all at once. That shift in understanding continues to shape where the field is headed: toward more targeted, more personalized, and increasingly non-opioid approaches to a problem that has occupied medicine for as long as medicine has existed.